
How to Choose Phlebotomy Supplies: A U.S. Laboratory Purchasing Guide
Summary
- U.S. laboratories should evaluate phlebotomy supplies according to patient safety, regulatory compliance, specimen quality, Workflow efficiency, and total cost rather than purchase price alone.
- Key purchasing decisions include selecting appropriate needles, blood collection tubes, safety devices, tourniquets, antiseptic products, transport materials, and supplies for special populations.
- Standardized specifications, supplier reliability, inventory controls, staff feedback, and performance data can reduce recollections, prevent waste, and improve laboratory turnaround time.
Phlebotomy supplies are among the most frequently used products in a clinical laboratory, hospital, physician office, outpatient draw center, and mobile testing service. A single collection may require a needle or collection set, tube holder, evacuated blood collection tubes, tourniquet, antiseptic, gauze, adhesive dressing, labels, transport packaging, and personal protective equipment. Because these items are used thousands or millions of times each year, purchasing decisions can have a significant effect on patient safety, laboratory accuracy, employee exposure risk, operational cost, and customer satisfaction.
For U.S. laboratories, purchasing phlebotomy supplies is not simply a matter of selecting the least expensive product. Supplies must be compatible with the laboratory’s analyzers, information systems, collection procedures, patient population, storage capacity, and regulatory obligations. A product that appears inexpensive may create hidden costs if it causes hemolysis, insufficient specimens, mislabeled tubes, Needlestick Injuries, recollections, delays, or disposal problems.
The scale of the issue is substantial. The Centers for Disease Control and Prevention has reported that approximately 70% of medical decisions depend on laboratory Test Results. This means that the quality of the specimen collected before testing is essential to clinical decision-making. At the same time, occupational Needlestick Injuries remain a recognized hazard in health care, and the Occupational Safety and Health Administration requires employers to use appropriate engineering and work-practice controls to reduce exposure to bloodborne pathogens. The right phlebotomy supplies support both objectives.
Patient Safety Should Be the First Purchasing Criterion
Every phlebotomy purchase should begin with a patient-safety assessment. The selected products should help reduce pain, accidental injury, contamination, specimen errors, and delays. A supply that saves a few cents per collection is not economical if it increases complications or requires the patient to return for another draw.
Needle design is especially important. Laboratories may need conventional straight needles, butterfly or winged infusion sets, safety needles, multi-sample needles, or products designed for difficult access and small-volume collections. Needle Gauge, length, bevel design, tubing configuration, and activation method can affect patient comfort and specimen quality. Smaller-gauge devices may be useful for pediatric or fragile veins, while larger-gauge devices may be preferred for certain blood bank, therapeutic, or high-volume collections.
Safety-engineered devices should be evaluated for actual usability rather than assumed effectiveness. A safety mechanism may be passive or require activation by the collector. Passive devices can reduce reliance on memory and technique, while active devices may require staff training and a deliberate activation step. Laboratories should determine whether activation can occur with one hand, whether the mechanism provides a clear visual or audible confirmation, and whether it works reliably while the device is being removed from the patient.
The National Institute for Occupational Safety and Health and OSHA have emphasized the importance of engineering controls in preventing sharps injuries. Under the Needlestick Safety and Prevention Act and OSHA’s Bloodborne Pathogens Standard, employers must consider safer medical devices and involve nonmanagerial employees who use the devices in the evaluation and selection process. This makes collector feedback an important part of procurement, not an optional administrative exercise.
Regulatory and Quality Requirements
U.S. laboratories must confirm that phlebotomy products are appropriate for their intended use and supported by the necessary regulatory documentation. Many collection products are medical devices regulated by the U.S. Food and Drug Administration. Depending on the product, the manufacturer may provide information concerning clearance, classification, intended use, performance characteristics, sterility, shelf life, and lot traceability.
Purchasing teams should maintain records showing why a product was selected, which specifications were reviewed, and how the product was approved for routine use. These records are valuable during internal audits, accreditation inspections, adverse-event investigations, and supplier reviews.
Laboratories operating under the Clinical Laboratory Improvement Amendments should consider how a new collection product affects preanalytical procedures. CLIA requirements emphasize accurate, reliable, and timely patient testing. A change in tube type, fill volume, additive, collection device, or transport system may require procedure revisions, validation, verification, staff training, or communication with testing departments.
Accrediting organizations and professional standards may also affect purchasing. The College of American Pathologists, The Joint Commission, CLSI documents, and state-specific requirements can influence expectations for specimen identification, collection order, transport, storage, safety, and quality management. Laboratories should review current requirements rather than relying on outdated purchasing specifications.
Manufacturers should be able to provide certificates of analysis, certificates of conformance, safety data sheets where applicable, lot information, product specifications, and instructions for use. The laboratory should also understand the supplier’s process for recalls, product changes, complaints, and field safety notices.
Specimen Quality and Tube Selection
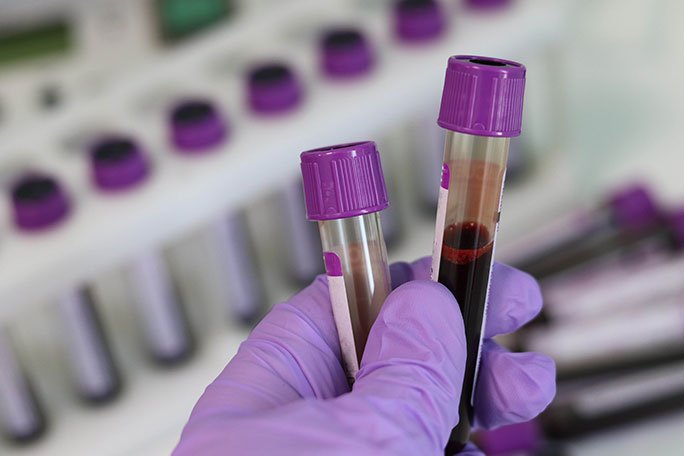
Blood collection tubes are not interchangeable simply because they have similar appearance or volume. Tube additives, fill ratios, material composition, stopper design, expiration dates, and compatibility with analyzers all influence test performance. A purchasing committee should review each tube by test category and specimen requirement.
Common tube categories include serum tubes, serum separator tubes, plasma separator tubes, Heparin tubes, EDTA tubes, citrate coagulation tubes, fluoride or glycolysis-inhibitor tubes, trace-element tubes, and specialized blood bank or molecular testing tubes. The color coding used by manufacturers is helpful but should never replace verification of the actual additive and intended use.
For coagulation testing, the ratio of blood to Sodium Citrate is particularly important. Underfilled citrate tubes can alter the ratio and potentially affect results. Laboratories should select tube sizes that match the patient population and test requirements. A standard adult tube may not be appropriate for pediatric patients, patients with difficult draws, or situations in which limited blood volume is available.
Vacuum strength also deserves attention. Excessive vacuum may contribute to vein collapse in small or fragile veins, while inadequate vacuum may produce short draws or require additional manipulation. Tube performance should be evaluated using the laboratory’s actual needles, holders, collection sets, transportation conditions, and analyzers.
Hemolysis is one of the most common causes of Specimen Rejection or unreliable Test Results. Published studies frequently identify hemolysis as a leading preanalytical error, and some laboratory quality programs report that preanalytical problems account for the majority of total laboratory errors. Although hemolysis is influenced by technique, it can also be affected by needle size, tube vacuum, collection systems, vigorous tube shaking, transport conditions, and processing delays.
Before approving a new tube, laboratories should compare hemolysis rates, clot rates, short draws, specimen leakage, gel separation, analyzer flags, and recollection frequency. A short pilot study using defined acceptance criteria is usually more informative than a general product demonstration.
Compatibility With Laboratory Equipment and Information Systems
Collection supplies must work with the laboratory’s existing equipment. This includes analyzers, aliquoting systems, centrifuges, automation tracks, tube readers, barcode printers, Pneumatic Tube Systems, and specimen management software. A tube that fits a manual centrifuge may not fit an automated line. A label that adheres to glass or plastic may not perform equally well under refrigeration, freezing, condensation, or pneumatic transport.
Laboratories should verify dimensions, tube volume, stopper design, cap color, barcode placement, label area, tube rigidity, and centrifugation requirements. The supplier should disclose whether tubes are compatible with the laboratory’s instruments and whether a validated adapter or carrier is required.
Automation compatibility is increasingly important as laboratories consolidate testing and process larger volumes. A small dimensional difference can cause tube jams, misreads, robotic-gripper failures, or sorting errors. These events can affect turnaround time and increase manual handling. Purchasing teams should involve laboratory automation specialists, phlebotomy supervisors, information technology personnel, and biomedical engineering staff before making a change.
Barcode and labeling requirements should also be addressed. The label must remain readable throughout collection, transport, centrifugation, refrigeration, and testing. It should not cover the tube fill line, additive information, or analyzer-readable areas. If the laboratory uses bedside or point-of-collection label printing, the purchasing review should include printer compatibility, adhesive performance, barcode symbology, and resistance to moisture and temperature changes.
Fit for the Laboratory’s Patient Population
A hospital serving adults may have very different supply requirements from a children’s hospital, oncology center, trauma facility, long-term care organization, or outpatient laboratory. Purchasing should reflect the patients who are actually being collected.
Pediatric and neonatal collections may require small-volume tubes, microcollection containers, lancets, heel-stick devices, small-gauge needles, low-dead-space collection sets, and products with clear minimum-volume specifications. Reducing blood loss is especially important for premature infants and patients who require frequent testing.
Geriatric Patients and individuals with fragile veins may benefit from low-volume tubes, smaller-gauge needles, winged sets, latex-free tourniquets, and devices designed to reduce vein collapse. Patients receiving chemotherapy, dialysis, or long-term intravenous therapy may have limited access sites or special collection restrictions.
Patients with obesity, dehydration, edema, burns, or difficult venous access may require longer needles, ultrasound-guided collection supplies, or specialized stabilization products. Laboratories should ensure that these supplies are available without allowing specialty products to become excessive or poorly controlled inventory.
Allergy and sensitivity considerations are also relevant. Latex-free products are widely used because latex exposure can cause Allergic Reactions, particularly in patients and employees with repeated health care contact. Laboratories should review the presence of latex, natural rubber, adhesives, alcohol, Chlorhexidine, fragrances, and other potential irritants in collection products.
Infection Prevention and Environmental Safety
Antiseptic products should be selected according to the collection procedure, patient condition, and organizational infection-prevention policy. Common options include isopropyl alcohol, Chlorhexidine preparations, povidone-iodine, and products designed for blood cultures. The appropriate preparation depends on the test and patient factors. For example, Blood Culture collections require a validated skin-disinfection process that differs from a routine Venipuncture.
Laboratories should confirm drying time, expiration, packaging integrity, single-use status, and compatibility with neonatal or allergy-sensitive patients. Individually packaged products may reduce contamination risk and improve convenience, while larger containers may create concerns about repeated access and expiration after opening.
Sharps containers must be appropriately sized, puncture resistant, closable, leak resistant, and positioned close to the point of use. A container that is too small may fill rapidly and require frequent replacement. A container that is too large may encourage overfilling or create unnecessary disposal expense. The selected container should allow users to discard devices without recapping, bending, or manipulating needles.
OSHA’s Bloodborne Pathogens Standard requires employers to use work practices and engineering controls that reduce employee exposure. Laboratories should therefore assess the entire collection system, including needle disposal, transport of specimens, spill response, protective clothing, gloves, eye protection, and waste segregation.
Environmental considerations are becoming more important in procurement. Laboratories can review packaging volume, recyclable materials, shipping materials, product weight, and disposal requirements. However, environmental goals should not compromise sterility, safety, shelf life, or Specimen Integrity. A total sustainability assessment should include manufacturing, transportation, storage, use, and disposal.
Supplier Reliability and Product Availability
A high-quality supply is not useful if it cannot be delivered consistently. The Covid-19 pandemic demonstrated how disruptions in manufacturing, transportation, raw materials, and global demand can affect medical supply availability. Laboratories should evaluate supplier resilience rather than relying on a single low-cost source for every critical item.
Important supplier questions include:
- What is the manufacturer’s average lead time, and how often does it change?
- Does the supplier maintain domestic distribution centers or alternative manufacturing locations?
- What is the supplier’s allocation policy during shortages?
- How much advance notice is provided for product discontinuations, packaging changes, or formulation changes?
- Can the supplier provide lot-level traceability and recall support?
- Are substitute products preapproved, or must they be evaluated during a shortage?
- What customer service and technical support are available after implementation?
Laboratories should identify critical supplies that require safety stock or dual sourcing. A dual-source strategy can reduce dependence on one manufacturer, but it may also create variation in tube performance, labels, color coding, or collection technique. If multiple products are approved, staff must be able to distinguish them and understand any differences in use.
Contracts should include service-level expectations, notification requirements, return procedures, expiration-date standards, damage policies, and pricing protections where possible. A supplier’s performance should be reviewed using measurable data such as fill rate, on-time delivery, back-order frequency, order accuracy, damaged shipments, and complaint response time.
Total Cost of Ownership
Unit price is only one component of the cost of a Phlebotomy Supply. Total cost of ownership includes purchasing, freight, storage, labor, training, equipment changes, waste disposal, product loss, recollection, and potential patient or employee injury.
For example, a tube that costs slightly more may be financially preferable if it reduces Specimen Rejection. The cost of a rejected specimen can include a new collection, phlebotomist time, registration or scheduling work, courier transport, additional supplies, delayed diagnosis, delayed treatment, and patient dissatisfaction. In inpatient settings, recollection can also extend length of stay or require additional staff time.
Laboratories should calculate cost per completed test or successful collection rather than cost per box. A useful analysis may include:
- Annual consumption by department and product type.
- Average product waste due to expiration, damage, contamination, or incorrect selection.
- Specimen Rejection and recollection rates associated with the product.
- Labor time required for setup, collection, labeling, and disposal.
- Training and implementation costs.
- Freight, storage, and inventory carrying costs.
- Costs related to safety incidents, complaints, and corrective actions.
Value analysis teams can compare competing products using a weighted scorecard. Patient safety, specimen quality, regulatory fit, supply continuity, and total cost should receive more weight than cosmetic packaging or minor purchasing convenience.
Inventory Management and Storage
Phlebotomy supplies occupy considerable storage space, particularly in high-volume organizations. Purchasing departments should examine product dimensions, case quantities, expiration dates, temperature requirements, and storage limits before approving an item.
First-expire, first-out inventory rotation is essential for products with expiration dates. Excessive purchasing may create waste, particularly when a test menu changes, a supplier updates a product, or a laboratory switches analyzers. Conversely, insufficient inventory may lead to emergency purchasing at a premium price or the use of unvalidated substitutes.
Inventory systems should establish par levels based on actual usage, lead time, seasonal demand, emergency requirements, and supplier reliability. Consumption data should be reviewed by location because a central warehouse may not reflect shortages in individual draw stations, emergency departments, inpatient units, or satellite clinics.
Storage conditions should be monitored according to manufacturer instructions. Heat, freezing, moisture, sunlight, and excessive pressure can damage packaging or affect product performance. Supplies should remain in their original packaging until use when sterility or product identification depends on that packaging.
Standardized products can simplify inventory, but excessive standardization may be inappropriate. A single needle, tube size, or Tourniquet may not meet the needs of every patient population. The goal should be controlled variety: enough options to support clinical requirements, but not so many that staff select products inconsistently or inventory becomes unmanageable.
Staff Usability and Training
Phlebotomists are the primary users of collection supplies and should be involved in product evaluation. Their experience can reveal problems that are not apparent in a purchasing specification. Examples include difficult safety activation, slippery tube surfaces, poorly fitting holders, tourniquets that do not release easily, labels that peel during transport, or packaging that is difficult to open while wearing gloves.
Product trials should include experienced collectors, new employees, inpatient staff, outpatient staff, and personnel who work with pediatric or difficult-access patients when relevant. Evaluation forms should assess ease of use, patient comfort, safety mechanism performance, visibility of fill lines, tube handling, packaging, and disposal.
Training is necessary whenever a new needle, collection set, tube, holder, label, or transport system is introduced. Even products that appear similar may have different activation steps or collection requirements. Training should cover product selection, order of draw, mixing requirements, minimum volumes, inversion counts, labeling, transport, and disposal.
The World Health Organization and CLSI have published widely used guidance emphasizing standardized blood collection practices. Following a consistent procedure helps reduce variation among collectors and improves the reliability of quality data. Training should be documented and competency should be assessed according to the laboratory’s policies and applicable requirements.
Measuring Performance After Purchase
Procurement should not end when the purchase order is issued. Laboratories should monitor product performance after implementation and compare results with the baseline. A product may perform differently in actual use than during a short demonstration.
Useful measures include:
- Specimen Rejection rate by collection location and collector group.
- Hemolysis rate by tube type, device, unit, and test category.
- Clotted or underfilled specimen frequency.
- Needlestick and sharps-injury reports.
- Patient complaints related to pain, bruising, or collection difficulty.
- Recollection frequency and the estimated cost of recollection.
- Stockouts, emergency orders, and expired inventory.
- Supplier fill rate, delivery accuracy, and complaint-resolution time.
Data should be reviewed fairly. A higher hemolysis rate may reflect patient mix, collector experience, transport conditions, or changes in testing volume rather than the supply alone. Nevertheless, trends can identify problems that require retraining, a procedure revision, or supplier investigation.
Laboratories may establish target thresholds for rejection and recollection based on their baseline performance, patient population, accreditation expectations, and organizational goals. Quality indicators should be reported to laboratory leadership and, where appropriate, nursing, medical staff, infection prevention, employee health, and Supply Chain teams.
Building an Effective Purchasing Process
An effective purchasing process brings together laboratory medicine, phlebotomy, nursing, infection prevention, occupational health, safety, Supply Chain, finance, information technology, and, when necessary, biomedical engineering. Each group sees different risks and costs.
The process can be organized into several stages:
- Define the clinical and operational need using utilization data, quality problems, patient feedback, or equipment changes.
- Write detailed specifications covering intended use, volume, additive, dimensions, safety features, sterility, labeling, packaging, and storage.
- Identify qualified suppliers and request technical documentation, samples, pricing, lead times, and quality records.
- Conduct a structured product trial in representative collection areas.
- Compare performance against predefined acceptance criteria and the current product.
- Complete regulatory, infection-prevention, safety, and compatibility reviews.
- Approve the product, update procedures, train staff, and establish inventory levels.
- Monitor post-implementation data and address problems through corrective action.
Purchasing committees should avoid making decisions solely through samples or presentations. A product may feel comfortable in the hand but fail to meet analyzer requirements. Another may have an attractive price but generate unacceptable Specimen Rejection. A balanced evaluation should combine direct observation, technical documentation, operational data, and financial analysis.
Questions to Ask Before Finalizing a Purchase
Before approving a Phlebotomy Supply, a U.S. laboratory should be able to answer several practical questions:
- Is the product appropriate for the intended patient population and test menu?
- Does it meet applicable FDA, OSHA, CLIA, accreditation, and organizational requirements?
- Is the safety feature effective, intuitive, and suitable for the actual collection Workflow?
- Has compatibility with analyzers, automation, labels, transport systems, and centrifuges been confirmed?
- What evidence supports acceptable specimen quality?
- What are the product’s storage, expiration, sterility, and disposal requirements?
- Can the supplier provide reliable delivery during periods of high demand or disruption?
- What is the total cost per successful collection or completed test?
- Have end users participated in the evaluation?
- What quality indicators will be monitored after implementation?
Conclusion
Phlebotomy supplies directly influence the quality and safety of laboratory operations. Needles, tubes, collection sets, antiseptics, labels, transport materials, and sharps containers should therefore be treated as essential components of the testing process rather than routine commodities.
For U.S. laboratories, the strongest purchasing decisions combine regulatory awareness, patient-safety priorities, specimen-quality data, staff input, equipment compatibility, supplier reliability, inventory discipline, and total-cost analysis. Federal requirements from OSHA and CLIA, device oversight by the FDA, recommendations from professional organizations, and local quality data all have a role in the decision.
The most economical product is not necessarily the one with the lowest invoice price. It is the product that consistently supports safe collections, accurate specimens, efficient Workflow, dependable availability, and acceptable long-term cost. By using structured evaluations and monitoring performance after implementation, laboratories can make purchasing decisions that protect patients, employees, and the integrity of every test result.
Disclaimer: The content provided on this blog is for informational purposes only, reflecting the personal opinions and insights of the author(s) on the topics. The information provided should not be used for diagnosing or treating a health problem or disease, and those seeking personal medical advice should consult with a licensed physician. Always seek the advice of your doctor or other qualified health provider regarding a medical condition. Never disregard professional medical advice or delay in seeking it because of something you have read on this website. If you think you may have a medical emergency, call 911 or go to the nearest emergency room immediately. No physician-patient relationship is created by this web site or its use. No contributors to this web site make any representations, express or implied, with respect to the information provided herein or to its use. While we strive to share accurate and up-to-date information, we cannot guarantee the completeness, reliability, or accuracy of the content. The blog may also include links to external websites and resources for the convenience of our readers. Please note that linking to other sites does not imply endorsement of their content, practices, or services by us. Readers should use their discretion and judgment while exploring any external links and resources mentioned on this blog.