
Serum Blood Collection Tubes: Red-Top, Gold-Top, and Tiger-Top Purchasing Guide
Summary
- Serum collection in the United States generally requires red-top tubes, gold or tiger-top serum separator tubes, or specialty serum tubes, depending on the laboratory test and analyzer.
- Gold-top serum separator tubes are often the most practical general-purpose choice, but tube additives, specimen volume, processing requirements, and laboratory validation must determine the final purchase.
- Purchasing decisions should account for FDA-cleared products, CLSI-based collection practices, CLIA requirements, expiration dates, storage conditions, employee safety, supply continuity, and total cost rather than unit price alone.
Choosing the correct blood collection tube is one of the most important purchasing decisions for a medical practice, laboratory, outpatient clinic, hospital, physician office laboratory, or Mobile Phlebotomy service. The tube affects specimen quality, clot formation, serum separation, analyte stability, laboratory processing, and ultimately the reliability of patient results.
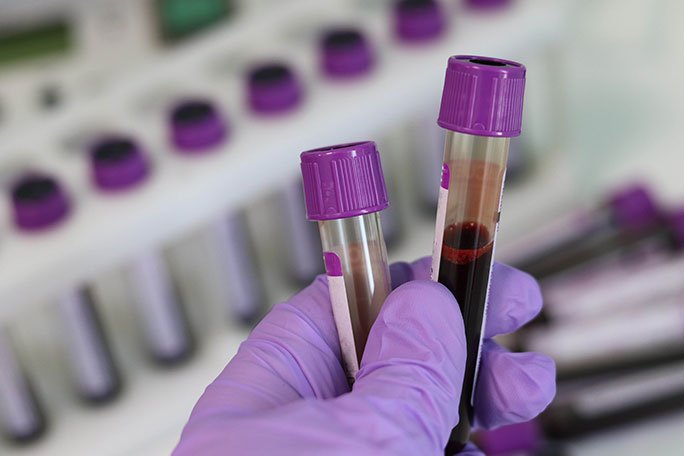
In the United States, the most common tube categories for serum collection are red-top tubes, gold-top serum separator tubes, and tiger-top serum separator tubes. Some laboratories also use specialty tubes designed for trace elements, Therapeutic Drug Monitoring, microbiology, immunology, or other tests that require a particular material or additive. There is no single “best” serum tube for every test. The correct purchase depends on the tests being performed, the receiving laboratory’s requirements, the collection setting, and the manufacturer’s instructions for use.
For many routine chemistry and serology applications, gold-top or tiger-top serum separator tubes, commonly called SST tubes, are the most efficient general-purpose option. They usually contain a Clot Activator and a polymer gel that forms a barrier between the serum and the clot after centrifugation. Red-top tubes, which generally contain no anticoagulant, may be preferable when a laboratory needs serum without gel or when a test method has been validated specifically for a plain tube.
Understanding Serum and Why Tube Selection Matters
Serum is the liquid portion of blood remaining after the specimen has clotted and the clot has been removed. It differs from plasma, which is obtained from blood collected in a tube containing an anticoagulant. Plasma retains fibrinogen and other clotting proteins, while serum generally does not.
This distinction is important because laboratory instruments and assays are validated for specific specimen types. A tube intended for plasma may produce an unacceptable specimen for a serum-based assay, even when the blood appears visually suitable. Conversely, collecting serum in an Anticoagulant tube can prevent clot formation and result in a specimen that does not meet the test’s requirements.
Tube selection can influence several preanalytical factors:
-
Whether the specimen clots completely before centrifugation.
-
Whether the specimen contains fibrin strands, microclots, hemolysis, or cellular contamination.
-
Whether the serum can be separated efficiently from the clot.
-
Whether the tube material or gel affects a particular analyte.
-
Whether the specimen remains stable during transport and storage.
-
Whether the tube is compatible with the receiving laboratory’s analyzer and processing system.
According to widely used laboratory quality principles, errors occurring before analysis account for a substantial share of total laboratory errors. Published studies commonly estimate that preanalytical problems represent approximately 46% to preanalytical issues can account for the majority of laboratory errors, with many reviews placing the proportion between 46% and 68%. Although estimates vary by study design and facility, the consistent conclusion is that collection, labeling, handling, transportation, and processing deserve as much attention as the analytical test itself.
The Main Serum Tube Options Available in the United States
Red-Top Tubes
Red-top tubes are traditionally used to collect serum without a gel barrier. Depending on the product, they may be made of glass or plastic. Plain red-top tubes generally contain no anticoagulant, although some plastic versions may include a Clot Activator. Buyers should never assume that every red-top tube is additive-free; the product label, package insert, and manufacturer specifications should be reviewed carefully.
Red-top tubes are commonly used for selected chemistry, serology, immunology, blood bank, and reference laboratory tests. They can be useful when the laboratory wants serum without Separator Gel, when a gel may interfere with an assay, or when the test instructions specifically call for a plain tube.
Glass red-top tubes naturally promote clotting through contact activation and may be selected by laboratories with established glass-tube procedures. Plastic red-top tubes are lighter and less likely to break, which may improve worker safety and shipping convenience. However, plastic products may rely on a Clot Activator to achieve acceptable Clotting Time.
When purchasing red-top tubes, confirm the following:
-
Whether the tube is truly plain or contains a Clot Activator.
-
Whether the tube is glass or plastic.
-
Whether the receiving laboratory accepts that specific tube type.
-
Whether the required serum volume can be obtained after clotting and separation.
-
Whether the tube is approved or cleared for the intended use in the United States.
Gold-Top Serum Separator Tubes
Gold-top SST tubes are among the most widely purchased tubes for routine serum testing. They typically contain a Clot Activator and a polymer gel. After the blood clots and the tube is centrifuged, the gel moves into position between the serum and the clot. This barrier helps reduce cellular contact with the serum during storage and transport.
Gold-top tubes are frequently used for routine metabolic panels, liver function testing, lipid testing, endocrine assays, immunoassays, Therapeutic Drug Monitoring, and many serology procedures. The exact list varies by laboratory and analyzer. A gold-top tube is not automatically acceptable for every serum test, particularly tests involving trace elements, drug levels, special proteins, or analytes known to interact with Separator Gel.
The principal advantage of an SST is Workflow efficiency. A properly filled and processed SST can reduce the need to transfer serum to another container. This can lower handling time and decrease the number of transfer steps, which may reduce opportunities for contamination, mislabeling, spills, or specimen loss.
However, SST tubes require correct technique. Blood must be allowed to clot fully before centrifugation. The tube should be gently inverted according to the manufacturer’s instructions, not vigorously shaken. Centrifuging too early can produce fibrin, gel disruption, or incomplete separation. In many settings, a clotting period of approximately 30 minutes is used for routine serum specimens, but the laboratory’s validated procedure and the tube manufacturer’s instructions take priority.
Tiger-Top Serum Separator Tubes
Tiger-top tubes are another common form of serum separator tube. The tube usually has a speckled or “tiger” colored cap and contains a Clot Activator and Separator Gel. Functionally, many tiger-top tubes are comparable to gold-top SST tubes, although color conventions and product formulations vary among manufacturers.
Buyers should not select a tiger-top tube solely because it looks similar to a gold-top tube. Different manufacturers may use different gel formulations, clot activators, tube dimensions, fill volumes, and recommended applications. A receiving laboratory may accept one product but reject another if the laboratory has not validated the substitute.
For organizations purchasing large quantities, it is useful to maintain a written equivalency list identifying which products have been approved for each test group. Substituting a tube based only on cap color can cause rejected specimens, recollection costs, and delays in patient care.
Specialty Serum Tubes
Some tests require specialty tubes rather than standard red-top or SST products. Examples may include tubes intended for trace-element testing, metals analysis, Therapeutic Drug Monitoring, hormone studies, molecular applications, or specialized immunology procedures.
Trace-element collection is particularly sensitive to contamination. A standard tube may contribute minute amounts of metals or other substances that interfere with testing. Laboratories may therefore require certified low-contamination tubes, royal blue-top tubes with a serum-specific additive, or another validated collection device. Royal blue is not a universal serum designation: some royal blue tubes contain sodium EDTA, Heparin, or other additives and are intended for plasma or whole blood. The additive must be verified before purchase.
Some therapeutic drug tests may require a red-top tube, while others may accept an SST. This depends on the drug, assay platform, laboratory validation, and timing of collection. Digoxin, lithium, anticonvulsants, immunosuppressants, and certain antibiotics are examples of test categories in which specimen requirements should be confirmed rather than inferred from the tube color.
Blood bank specimens generally require EDTA tubes rather than serum tubes for many procedures, including antibody screening and compatibility testing. These are not serum collection tubes and should not be substituted with red-top or gold-top products. A practice that performs both routine chemistry and blood bank collection should maintain separate inventories and clear collection instructions.
How Much Tube Volume Should You Purchase?
Common serum tube sizes include approximately 3.5 mL, 4 mL, 5 mL, 7 mL, and 8.5 mL, although exact capacities vary by manufacturer. Pediatric and low-volume tubes may hold less than 2 mL. The correct size depends on the required serum volume, patient population, draw requirements, and analyzer instructions.
Purchasing only large tubes may create unnecessary problems in pediatrics, geriatrics, oncology, dialysis, and other populations in which blood conservation is important. Purchasing only small tubes may be inefficient for patients requiring multiple chemistry and serology tests. A mixed inventory is often more practical.
When estimating volume, remember that serum yield is lower than the original whole-blood volume because the clot occupies space. A tube filled to only half its intended volume may also clot differently or provide insufficient serum. Laboratories should specify the minimum acceptable volume for each test and identify whether dead volume is required by the analyzer or aliquoting system.
Manufacturers commonly describe tubes by nominal draw volume, but the label may also show a fill line. Staff should be trained to recognize underfilled specimens and to follow the receiving laboratory’s rejection criteria. Inadequate volume is a frequent reason for recollection, especially when multiple tests are ordered from one tube.
What to Check Before Purchasing Serum Tubes
Laboratory Test Menus and Receiving-Laboratory Requirements
The first purchasing step is to obtain the test directory or specimen-collection guide used by the laboratory that will perform the testing. This document should identify the preferred tube, acceptable alternatives, minimum volume, processing instructions, stability limits, transport temperature, and special handling requirements.
If specimens are sent to several laboratories, create a matrix that maps each test to its required tube. A gold-top SST may be accepted for a routine comprehensive metabolic panel but not for a specialized Toxicology test. A red-top tube may be suitable for one reference laboratory and unacceptable for another.
Regulatory and Quality Requirements
In the United States, laboratories performing human testing are generally subject to the Clinical Laboratory Improvement Amendments, commonly called CLIA. CLIA requirements emphasize accurate, reliable, and timely testing, including appropriate specimen collection and handling. The Centers for Medicare and Medicaid Services administers the CLIA program, while accreditation organizations such as the College of American Pathologists may impose additional quality expectations.
Collection tubes are medical devices. Buyers should confirm that products are legally marketed for their intended use in the United States and that the supplier can provide current labeling, instructions for use, lot information, and documentation of quality controls. Depending on the product and its intended use, regulatory status may involve FDA clearance, exemption, registration, or another applicable pathway. The purchasing department should request documentation rather than relying on advertising language.
CLSI standards are also widely used as technical references for venous blood collection, tube order, specimen handling, and quality practices. A facility does not necessarily need to purchase a specific brand because a CLSI document mentions a tube type. However, its collection procedure should be consistent with applicable laboratory standards and the validated requirements of the testing laboratory.
Tube Materials and Additives
Tube material can influence breakage risk, centrifugation, transport, and analyte compatibility. Glass tubes may provide certain clotting characteristics but present a breakage and sharps risk. Plastic tubes are lighter and generally safer for routine transport, but they may use clot activators or require specific processing procedures.
Separator Gel can improve Workflow, but gel is not chemically neutral for every application. Some drugs, hormones, vitamins, and other analytes may adsorb to or interact with gel under particular conditions. The laboratory should determine whether the gel is acceptable for the intended testing platform.
Clot activators also vary. Silica-based particles or other activator formulations may affect Clotting Time and performance in patients with abnormal coagulation or high hematocrit values. Staff should follow the manufacturer’s inversion instructions and wait the validated amount of time before centrifugation.
Expiration Dates and Storage
Blood collection tubes have expiration dates because vacuum performance, additives, gel characteristics, and stopper integrity can change over time. Purchasing large quantities solely to obtain a lower price can result in expired inventory, particularly for specialty tubes with low usage.
Stock should be rotated using the first-expire, first-out method. Receiving staff should inspect cartons for damage, moisture, broken packaging, incorrect products, and short dating. Tubes should be stored within the temperature and humidity range specified by the manufacturer. Excessive heat, freezing, or prolonged exposure to unsuitable conditions may affect vacuum and additive performance.
Facilities should track usage by product number and lot number. A basic inventory system can identify monthly consumption, seasonal changes, back-order risk, and products approaching expiration. For high-volume clinics, barcode-based inventory management may reduce manual counting and improve lot traceability.
Recommended General Purchasing Strategy
For a typical United States outpatient practice collecting routine serum specimens, the starting inventory often includes a primary SST product and a smaller quantity of plain red-top tubes. The exact balance depends on the test menu. If most specimens are sent for routine chemistry and immunoassay testing, gold-top or tiger-top SST tubes may represent the majority of purchases. If the practice sends specialized tests to laboratories that prohibit gel, red-top tubes may be necessary.
A practical purchasing plan can be organized as follows:
-
List every serum-based test ordered by the practice during the previous 6 to 12 months.
-
Identify the performing laboratory and obtain its current tube requirements for each test.
-
Group tests into routine SST, plain serum, specialty serum, and non-serum categories.
-
Select the smallest number of validated tube products that can meet the test menu without unsafe substitutions.
-
Choose appropriate adult, pediatric, and low-volume sizes based on patient demographics.
-
Establish minimum and maximum inventory levels using actual monthly consumption and supplier lead time.
-
Evaluate total cost, including shipping, recollection, waste, storage, and processing labor.
-
Approve a backup product only after the laboratory confirms that it is acceptable for the intended tests.
Unit price should not be the only purchasing criterion. A tube that costs a few cents less may be more expensive overall if it causes clotting failures, gel problems, analyzer errors, recollections, or delayed results. In outpatient settings, a recollection may involve clinical staff time, patient inconvenience, transportation costs, and delayed treatment. For this reason, the total cost of ownership is more informative than the catalog price.
Collection and Processing Practices That Protect Serum Quality
Even the correct tube can produce an unacceptable specimen when collection technique is poor. Staff should verify the patient’s identity using the facility’s approved procedure, confirm the requested tests, label the tube in the patient’s presence, and document collection time when required.
The standard order of draw is designed to reduce additive carryover between tubes. A commonly used order begins with Blood Culture bottles, followed by citrate tubes, serum tubes, Heparin tubes, EDTA tubes, and fluoride or glycolytic inhibitor tubes. The exact procedure should follow the current laboratory policy and applicable CLSI guidance. If a serum tube is collected after a tube containing an additive, contamination can affect results.
Serum tubes should be gently inverted the number of times specified by the manufacturer. Vigorous shaking can cause hemolysis. Tubes should remain upright while clotting whenever possible. The laboratory should define the required clotting interval, centrifuge speed or relative centrifugal force, centrifugation time, and temperature.
Hemolysis is one of the most common specimen-quality problems. National and international laboratory surveys have repeatedly identified hemolyzed specimens as a leading cause of Specimen Rejection. Hemolysis can increase or decrease reported concentrations of analytes and may interfere with photometric, electrochemical, or immunoassay methods. Proper needle selection, avoiding excessive suction, allowing antiseptic to dry, and using gentle handling can reduce risk.
The specimen should be inspected after centrifugation. Serum that is visibly hemolyzed, lipemic, icteric, contaminated with cells, or affected by fibrin may require consultation with the laboratory. A gel barrier that is incomplete, displaced, or mixed with serum may also indicate a processing problem.
Common Purchasing Mistakes to Avoid
-
Buying by cap color alone. Cap colors are useful visual identifiers, but they are not universal technical standards. Two tubes with the same color may contain different additives.
-
Assuming every gold-top tube is interchangeable. Gel, Clot Activator, draw volume, and tube dimensions can vary by manufacturer.
-
Using SST tubes for every serum test. Some assays require plain serum or a specialty low-contamination tube.
-
Ignoring pediatric and low-volume needs. Large tubes may result in excessive blood loss or insufficient collection from difficult draws.
-
Overbuying specialty tubes. Low-volume products can expire before use when purchased in excessive quantities.
-
Substituting a product during a shortage without verification. A replacement should be approved by the performing laboratory and documented in the procedure manual.
-
Failing to evaluate transport requirements. A tube that works at the collection site may not be suitable for extended shipment or pneumatic-tube transport.
-
Neglecting staff training. Correct tube selection cannot compensate for incorrect order of draw, inadequate clotting, or improper centrifugation.
How Many Tubes Should a Facility Keep in Stock?
Inventory levels should be based on actual utilization rather than a universal number. A small physician office may use a few hundred serum tubes per month, while a hospital outpatient laboratory may use thousands each week. The facility should calculate average monthly usage, add a safety stock based on supplier lead time, and account for expiration.
A useful formula is average weekly usage multiplied by the number of weeks required for replenishment, plus a safety margin for unexpected demand. The safety margin should reflect local risk. A rural clinic with one supplier and long delivery times may need more reserve stock than a metropolitan clinic with multiple distributors.
Facilities should also monitor national and regional supply conditions. The United States has experienced periodic shortages and allocation constraints involving collection tubes, Blood Culture bottles, needles, syringes, and other medical supplies. Public health emergencies, transportation disruptions, raw-material shortages, manufacturing interruptions, and sudden increases in testing volume can all affect availability. Maintaining an approved secondary product and a documented substitution process can improve resilience.
Questions to Ask a Supplier
Before placing a substantial order, purchasing staff should request clear product information from the supplier and manufacturer. Important questions include:
-
What additive, Clot Activator, or Separator Gel does the tube contain?
-
Is the product intended for serum, plasma, whole blood, or a specific test category?
-
What are the nominal draw volume and minimum fill requirements?
-
What are the recommended inversion, clotting, centrifugation, and storage conditions?
-
What is the remaining shelf life at shipment?
-
How are lot numbers and expiration dates identified on individual cartons?
-
What quality and regulatory documentation is available?
-
Are smaller pediatric or low-volume sizes available?
-
What is the supplier’s back-order, allocation, and substitution policy?
-
Can the supplier provide consistent products across multiple purchase orders?
It is also wise to ask whether the tubes are compatible with the practice’s centrifuges, racks, automated accessioning equipment, pneumatic-tube system, and Laboratory Information System. Physical compatibility can be just as important as chemical compatibility.
Final Recommendation
For most United States practices collecting routine serum samples, a validated gold-top or tiger-top serum separator tube is often the most versatile primary purchase. These tubes commonly support routine chemistry, immunoassay, and many serology workflows while simplifying separation and reducing transfer steps.
A supply of red-top tubes should usually be maintained for tests that require plain serum or that are not approved for Separator Gel. Specialty serum tubes should be purchased only when the test menu and performing laboratory specifically require them. Royal blue, gray, lavender, green, and light-blue tubes should not be treated as serum tubes merely because they are available; their additives and intended specimen types are different.
The final decision should be made jointly by the laboratory director, clinical leadership, phlebotomy manager, quality department, and purchasing team. The best tube is the one validated for the intended test, consistently available, correctly sized, properly labeled, compatible with processing equipment, and supported by clear handling instructions.
In short, begin with the laboratory’s test requirements rather than the tube catalog. Select SST tubes for appropriate routine serum applications, retain plain red-top tubes where required, add specialty products only for validated indications, and manage inventory with attention to expiration, supply continuity, and total cost. This approach supports accurate testing, reduces recollections, and helps protect both patients and laboratory staff.
Disclaimer: The content provided on this blog is for informational purposes only, reflecting the personal opinions and insights of the author(s) on the topics. The information provided should not be used for diagnosing or treating a health problem or disease, and those seeking personal medical advice should consult with a licensed physician. Always seek the advice of your doctor or other qualified health provider regarding a medical condition. Never disregard professional medical advice or delay in seeking it because of something you have read on this website. If you think you may have a medical emergency, call 911 or go to the nearest emergency room immediately. No physician-patient relationship is created by this web site or its use. No contributors to this web site make any representations, express or implied, with respect to the information provided herein or to its use. While we strive to share accurate and up-to-date information, we cannot guarantee the completeness, reliability, or accuracy of the content. The blog may also include links to external websites and resources for the convenience of our readers. Please note that linking to other sites does not imply endorsement of their content, practices, or services by us. Readers should use their discretion and judgment while exploring any external links and resources mentioned on this blog.